
Quick answer: Healthcare RCM connects patient access, clinical documentation, claims administration, and financial follow-up. Medical billing is part of RCM; the broader cycle starts before care and continues until outstanding balances are resolved and performance is reviewed.
Revenue cycle management (RCM) in healthcare is the coordinated process of managing a patient’s financial journey, from appointment scheduling and insurance verification through clinical documentation, medical coding, claims, reimbursement, and collections.
This 2026 guide explains RCM in medical billing, the 14 common steps of the healthcare revenue cycle, practical ways to prevent claim problems, and the metrics practices can use to evaluate financial performance.
- What Is RCM in Medical Billing?
- How the Healthcare RCM Cycle Works
- The 14 Steps of RCM
- Why RCM Matters
- Common RCM Challenges
- Important RCM KPIs
- How to Improve the RCM Process
- A Realistic RCM Workflow Example
- RCM Software vs. Outsourcing
- Frequently Asked Questions
- Sources & Editorial Note
- TrueCare RCM Services
What Is RCM in Medical Billing?
RCM in medical billing is the end-to-end process healthcare organizations use to manage insurance coverage checks, accurate charge capture, coding, claims, payment posting, denial resolution, patient balances, and financial reporting.
Medical billing concentrates on converting documented services into claims and collecting payments. RCM includes that work but begins earlier, with registration and eligibility verification, and extends further into operational analysis and process improvement.
RCM vs. Medical Billing: What Is the Difference?
| Aspect | Medical billing | Revenue cycle management |
|---|---|---|
| Main focus | Claims, payer payments, and patient balances | The complete financial workflow surrounding patient care |
| Starting point | Usually documentation and charge preparation | Scheduling, registration, and pre-service verification |
| Core tasks | Claim submission, payment posting, follow-up | Patient access, authorization, coding, billing, denials, A/R, reporting |
| Success measures | Claim accuracy and payment resolution | Financial performance, denial trends, collection efficiency, patient experience |
For practices seeking operational support rather than an educational explanation, see TrueCare RCM’s revenue cycle management services and medical billing and coding services.
How Does the Healthcare RCM Cycle Work?
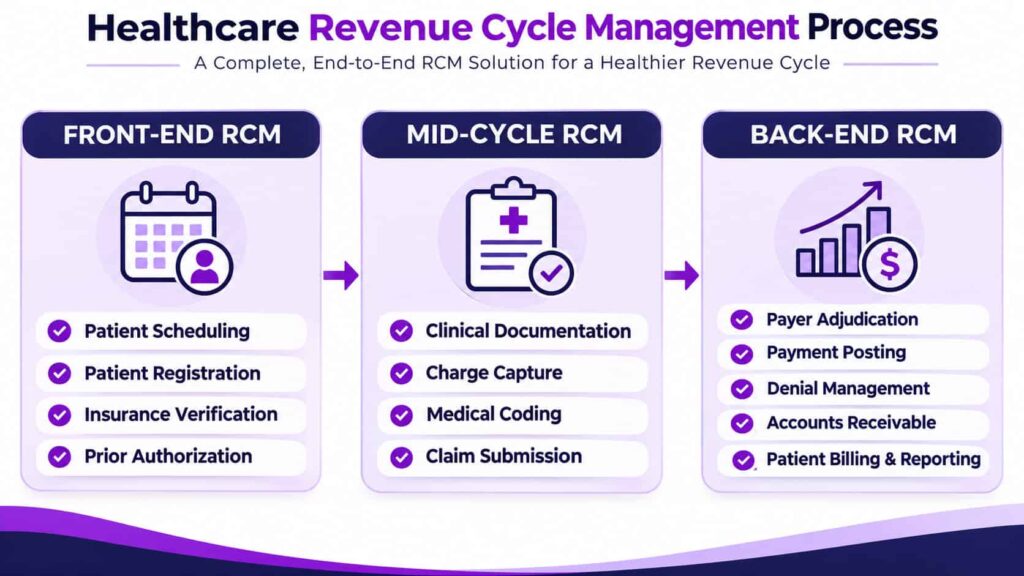
The healthcare revenue cycle is commonly discussed in three broad phases. These phases overlap in real organizations, and the exact steps vary by care setting, payer, and practice-management system.
Front-End RCMScheduling, registration, insurance eligibility, benefits, referrals, and authorizations.
Mid-Cycle RCMClinical documentation, charge capture, medical coding, claim checks, and submission.
Back-End RCMPayer adjudication, payments, denials, accounts receivable, patient billing, and reporting.
Important: A verified eligibility response or approved prior authorization is not a promise of payment. Final reimbursement depends on applicable benefits, documentation, coding, payer policies, and claim adjudication.
The 14 Steps of Revenue Cycle Management in Healthcare
There is no single, universally mandated 14-step RCM sequence. This practical framework organizes common healthcare revenue cycle activities into fourteen connected steps, from first contact through financial review.
1. Patient Pre-Registration and Appointment Scheduling
Staff collect the patient’s name, contact information, reason for visit, and available insurance details. Accurate scheduling and pre-registration make it easier to identify missing information before the appointment.
Example: A specialty clinic collects the patient’s insurance plan information while scheduling a new consultation.
2. Insurance Verification and Eligibility
The practice checks active coverage, plan benefits, network participation, deductibles, copayments, and other relevant requirements. Eligibility checks reduce preventable coverage surprises but cannot guarantee payment.
Example: The front desk discovers the scheduled clinician is out of network and contacts the patient before the visit.
3. Prior Authorization and Referral Management
Some services require a referral or payer authorization. The team reviews plan requirements, gathers supporting clinical documentation, submits requests, and records status and approved service details when applicable.
Example: An imaging order is checked against the patient’s plan to determine whether advance approval is necessary.
4. Patient Registration and Check-In
Staff reconfirm demographics and coverage, collect required documents, explain known financial responsibility, and correct changes made since scheduling.
Example: A patient provides a replacement insurance card; registration updates the payer and subscriber details before the encounter is billed.
5. Clinical Documentation and Charge Capture
Clinical records describe services actually performed, while charge capture identifies potentially billable procedures and visits. Missing documentation or omitted charges can create both billing and compliance problems.
Example: Following an office visit, the clinician finalizes the note and the charge capture team checks it for completeness.
6. Medical Coding and Charge Posting
Coders use documented services to determine applicable diagnosis and procedure codes, following current ICD-10-CM, CPT, HCPCS, and payer rules. Charges and supported modifiers are then posted to the billing system.
Example: A coding reviewer checks whether a separately documented procedure supports distinct billing under the applicable edit rules.
7. Claim Scrubbing and Submission
Claims are checked for patient and provider identifiers, code consistency, missing fields, and applicable payer edits. Valid claims are submitted within required deadlines, commonly through electronic claim workflows.
Example: A claim edit flags a missing subscriber identifier before submission, allowing the team to correct it.
8. Clearinghouse Validation and Payer Adjudication
A clearinghouse may accept, reject, or route the claim based on formatting and data checks. The payer then evaluates coverage, medical necessity, coding, and contract terms to determine payment or denial.
Example: A cleanly transmitted claim reaches the insurer, where payment is evaluated against the patient’s plan.
9. Payment Posting and Reconciliation
The billing team records insurance payments, contractual adjustments, denial reasons, and patient responsibility using remittance information. Reconciliation helps identify posting errors, unexpected reductions, and unresolved balances.
Example: An electronic remittance shows a deductible adjustment, which is recorded before a patient statement is prepared.
10. Denial Review, Correction, and Appeals
Denied claims are investigated by reason, payer, and filing deadline. Staff determine whether additional records, correction, reconsideration, or a formal appeal is appropriate. Rejection and denial are different stages and should be tracked separately.
Example: The payer requests supporting records; the team checks appeal rules and submits the requested documentation when appropriate.
11. Accounts Receivable (A/R) Follow-Up
A/R teams monitor unpaid claims and patient balances, review claim status, investigate aging accounts, and follow up before deadlines expire. Prioritization helps address claims most likely to need action.
Example: A claim beyond the normal processing window is reviewed using the payer portal and remittance history.
12. Patient Statement Processing
After payer adjudication, billing staff calculate applicable patient responsibility and issue understandable statements that reflect payments, adjustments, and available ways to ask questions.
Example: A deductible balance appears on the payer’s remittance; the statement explains the amount owed without confusing the patient with the original charge.
13. Patient Payments and Account Resolution
Practices receive and record patient payments, discuss approved payment options, and reconcile remaining balances. Collection activities should respect applicable laws, contracts, and patient protections.
Example: A patient contacts the billing team for clarification and chooses an available payment method.
14. Reporting, Auditing, and Continuous Improvement
Finance and billing leaders evaluate denials, A/R aging, collection trends, and coding quality. Audit findings are translated into better workflows, staff training, and escalation rules.
Example: Repeated eligibility denials prompt a review of intake scripts and verification procedures.
Why Is Revenue Cycle Management Important?
Effective RCM supports predictable operations, but it does not eliminate every denied claim or guarantee payment. Its value comes from helping practices recognize and address problems throughout the patient’s financial journey.
- Fewer preventable errors: Consistent registration, documentation, coding, and claim checks reduce avoidable rework.
- Better cash-flow visibility: Payment posting and A/R monitoring reveal delays before balances become difficult to collect.
- Clearer patient communication: Accurate cost information and readable statements reduce confusion.
- Improved operational coordination: Front-desk, clinical, coding, and billing teams work from consistent data.
- Stronger compliance processes: Documentation checks, audits, and payer-policy reviews support appropriate billing practices.

Common RCM Challenges and How to Address Them
1. Eligibility and Patient Data Errors
Outdated coverage, incorrect identifiers, and missing registration details can trigger claim rejection or nonpayment. Use standardized registration fields, verify coverage for the relevant date of service, and document unresolved questions.
2. Incomplete Documentation and Coding Mistakes
Unsupported codes, missing clinical details, or inappropriate modifiers can lead to denials and compliance risks. Use documented coding policies, targeted audits, and feedback between coders and clinicians. CMS publishes official ICD-10-CM and National Correct Coding Initiative resources for relevant Medicare billing requirements.
3. Prior Authorization and Medical Necessity Problems
Coverage requirements vary by payer and procedure. Maintain a procedure-specific authorization workflow and confirm the authorization details, clinical records, dates, and plan conditions before services occur when required.
4. Rejections, Denials, and Timely-Filing Risks
A rejected claim may not have entered payer adjudication; a denied claim has generally been processed but not paid as submitted. Track each separately, use payer-specific work queues, and resolve the root cause rather than repeatedly resubmitting the same error.
5. Aging Accounts and Payment Variances
Unworked A/R, underpayments, and posting discrepancies can obscure actual financial performance. Review aging by payer and age band, reconcile remittances, and escalate accounts approaching filing or appeal deadlines.
6. Staffing, System, and Communication Gaps
Disconnected software and inconsistent handoffs between teams create rework. Document ownership, train staff, and review recurring issues in cross-functional meetings. Automation should support human review rather than replace it for complex payer decisions.
Which Revenue Cycle Management KPIs Should Practices Track?
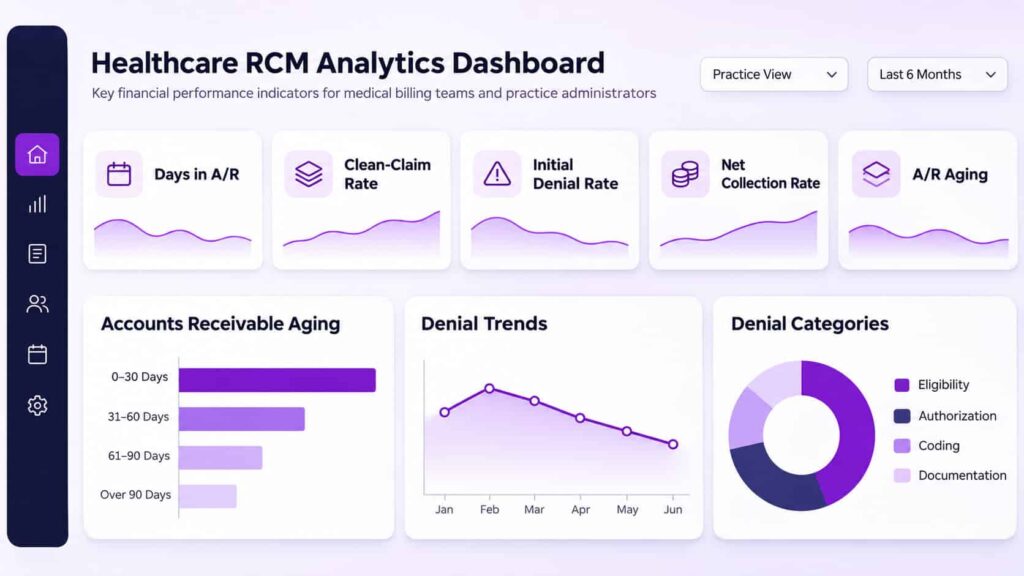
RCM KPIs help practice leaders understand claims performance, payment delays, and potential revenue leakage. Use consistent definitions and denominators when comparing periods, sites, specialties, or payers.
| KPI | What it indicates | Practical measurement approach |
|---|---|---|
| Days in A/R | How long receivables remain outstanding | Often estimated as qualifying net A/R divided by average daily net charges, using a consistently defined period |
| Clean-Claim Rate | Claims clearing defined first-pass validation | Claims accepted without correction ÷ submitted claims × 100; document whether measured at clearinghouse or payer level |
| Initial Denial Rate | Share of claims denied during initial adjudication | Initially denied claims ÷ initially adjudicated claims × 100; define count- versus dollar-based measurement |
| Net Collection Rate | Collection performance against collectible reimbursement | Payments collected ÷ eligible charges after contractual adjustments × 100, with exclusions and periods documented |
| A/R Aging | Where unpaid balances are concentrated | Segment unpaid balances into time bands, such as 0–30, 31–60, 61–90, and over 90 days |
| Denial Reasons | Patterns driving avoidable rework | Group denials by category, payer, specialty, and root cause; monitor trends over time |
KPI definitions are not identical across software vendors and organizations. Confirm your practice’s measurement rules before using outside benchmarks or comparing performance over time.
For a practical implementation starting point, see our RCM checklist for small practices.
How to Optimize the RCM Process
Successful revenue cycle optimization depends on repeatable controls and accountable teams, not only faster claim submission. These improvements can be introduced in stages:
- Standardize intake: Check demographic fields, payer information, network status, and benefits before encounters.
- Track authorizations: Record approval status, service limitations, expiration dates, and required supporting records.
- Improve documentation: Give clinicians and coding teams clear guidance on missing or inconsistent records.
- Validate claims: Apply appropriate claim edits, review rejection reports, and monitor timely-filing limits.
- Analyze denials: Segment denials by cause and payer, then fix repeatable upstream problems.
- Work A/R systematically: Prioritize accounts based on age, payer response, deadlines, and available next actions.
- Review metrics routinely: Compare results using consistent definitions and assign owners to improvement actions.
Specialized support may help with individual workflows, such as eligibility and benefits verification, prior authorizations, and denial management.
Real-World RCM Example: A Patient’s Office Visit
The following fictional, simplified example illustrates the workflow; it is not a TrueCare client case study or a promise of reimbursement.
Before the visit: A patient books a specialist appointment. Staff verify active coverage and identify any referral or authorization requirement.
At the visit: Registration confirms the patient’s information. The clinician documents the examination and services performed.
After the visit: Coding staff review the record, charges are entered, and a validated claim is submitted to the payer.
At adjudication: The insurer processes the claim and sends remittance information showing payment, adjustments, and any patient responsibility.
At account resolution: The billing team posts payment, follows up on a missing amount if necessary, issues an accurate patient statement, and closes or escalates the balance.
For improvement: Practice leaders review rejection, denial, and A/R trends to prevent similar issues during future visits.
This illustrates why RCM is broader than claim submission: an error during registration can affect a claim weeks later, while accurate payer responses and payment posting determine whether the account is fully resolved.
RCM Software vs. Outsourced Revenue Cycle Management Services
RCM software helps teams automate and organize processes such as eligibility checks, claim submission, edits, payment posting, denial work queues, and reporting. Outsourced RCM services provide people and workflows to perform some or all of those functions on a practice’s behalf.
| Approach | Typical responsibility | What to evaluate |
|---|---|---|
| In-house team with software | Practice staff operate billing workflows using EHR, practice management, and clearinghouse tools | Staff expertise, integrations, training, security, reporting, and total cost |
| Outsourced RCM | External team manages contracted billing tasks and payer follow-up | Scope of service, reporting transparency, escalation process, security, ownership, and accountability |
| Hybrid model | Practice retains selected tasks while a partner handles specified workflows | Clear handoffs, data access, reconciliation, service levels, and shared metrics |
Automation and artificial intelligence may support coding review, exception detection, and work prioritization; they still require oversight, tested controls, and attention to privacy and payer requirements. Vendor brand names alone do not demonstrate the quality of an RCM workflow.
Frequently Asked Questions About RCM in Healthcare
Revenue cycle management is the coordinated process healthcare practices use to manage patient registration, coverage verification, coding, claims, payments, denials, collections, and reporting from first contact through final financial resolution.
- It includes front-end, mid-cycle, and back-end workflows.
- It helps teams track where claims or payments need attention.
RCM covers the entire patient financial journey, while medical billing focuses on preparing and submitting claims, recording payments, and following up; billing is therefore one part of broader revenue management.
- Billing starts primarily with documented charges and claims.
- RCM also includes scheduling, eligibility, authorization, analytics, and process improvement.
The healthcare RCM cycle begins with registration and eligibility, proceeds through documentation, coding, and claims, then continues through payer decisions, payment posting, denial resolution, patient billing, and ongoing performance review.
- Different healthcare organizations may group steps differently.
- Errors early in the cycle can affect downstream reimbursement.
There is no universally mandated number of RCM steps; this guide organizes common activities into fourteen practical stages, but actual workflows vary by organization, insurance payer, and specific care setting.
- Some organizations combine registration and verification into one stage.
- Others separate authorization, appeals, financial counseling, and audit functions.
A clean claim contains complete, accurate information that passes applicable initial validation without correction, but it may still be denied later because of specific coverage, medical documentation, or payer requirements.
- Define whether clean-claim performance is measured at clearinghouse or payer acceptance.
- Clean does not mean automatically payable.
RCM teams commonly monitor denial rates, days in accounts receivable, clean claim rates, net collection rates, and aged balances to identify recurring payment delays, process errors, and overall financial trends.
- Use the same calculation definitions across reporting periods.
- Review payer-level trends rather than relying only on one organization-wide average.
Practices can reduce preventable denials through eligibility checks, accurate clinical documentation, appropriate coding, claim validation, timely follow up, and root cause reviews, although individual insurer decisions still influence final payment.
- Separate clearinghouse rejections from adjudicated denials.
- Target recurring causes such as missing authorizations or outdated demographic data.
An RCM company may help healthcare practices manage eligibility, coding, claims, payment posting, denial review, accounts receivable, and reporting; the exact scope depends on contractual agreements and individual practice needs.
- Some partners also offer prior authorization, credentialing, and patient billing.
- Ask how reporting, data security, responsibilities, and escalation procedures are handled.
Sources and Editorial Transparency
This educational guide is based on standard US healthcare billing workflows and the following public CMS resources. Coding, reimbursement, coverage, and filing rules change; verify current requirements for the payer, plan, service, and date of care.
- CMS: ICD-10 coding resources and current updates
- CMS: Medicare NCCI Policy Manual
- CMS: Health Care Payment and Remittance Advice
- CMS: HIPAA adopted transaction standards and code sets
Editorial note: This page is educational and is not a substitute for official coding manuals, current payer policy, legal advice, or a documented claim review. Any named author or expert reviewer should be a real person with verifiable responsibilities and qualifications.
How TrueCare RCM Supports Healthcare Providers
TrueCare RCM offers revenue cycle management services and related medical billing support for US healthcare practices. Depending on the agreed scope, services may include eligibility review, claims administration, payment posting, denial follow-up, A/R management, and reporting. If your practice is reviewing claim denials, unpaid balances, or billing workflow performance, speak with the team about your needs and the services available for your specialty.






